Safety depends on whether the cyst is confidently identified, infected, enlarging, recurrent, or associated with suspicious ultrasound findings. By comparing observation, infection treatment, aspiration, and the Sistrunk procedure, you can identify which questions to ask before choosing care for a child or adult.
Key takeaways
- Observe a small, symptom-free simple cyst only with reliable ultrasound and scheduled follow-up.
- Get prompt assessment for an enlarging, adult-onset, infected, solid or symptomatic neck mass.
- Ask whether ultrasound, thyroid testing and needle sampling are needed before surgery.
- The Sistrunk procedure removes the cyst and its tract, unlike aspiration or simple excision.
Which option is safer for a child or adult: observation or surgery?
Observation is usually the lower immediate-risk choice for a small, symptom-free cyst when ultrasound confidently shows a simple cyst with no solid component, infection, airway problem, or swallowing difficulty, and you can attend follow-up. An adult-onset or enlarging neck mass needs assessment, not an assumption that it is harmless.
| Option | Safer when | Main concern |
|---|---|---|
| Observation | A child or adult has an uncomplicated cyst, reliable follow-up, and reassuring ultrasound | Enlargement, infection, abscess, skin drainage, or missed diagnostic uncertainty |
| Surgery | The cyst is painful, enlarging, persistent, repeatedly infected, draining, or affecting swallowing or breathing | Anaesthesia, bleeding, wound problems, scar, nearby-structure injury, and recurrence |
For children, observation is reasonable when the diagnosis is secure and follow-up is dependable; recurrent infection or uncertainty favours surgery. For adults, persistent masses deserve a lower threshold for ultrasound, cytology, and definitive treatment because malignancy must be excluded carefully.
The safer choice in thyroglossal cyst surgery or observation in Mumbai depends on diagnosis, anatomy, infection control, thyroid assessment, and follow-up—not on automatically operating or automatically waiting. The thyroglossal cyst treatment options should be discussed with an ENT or head-and-neck specialist.
An infected cyst usually needs antibiotics and abscess drainage first; definitive surgery follows after acute inflammation settles. Rapid growth, fever, redness, new pain, drainage, or breathing or swallowing difficulty requires prompt review.
When is observation reasonable, and what risks remain?
Observation is reasonable only when ultrasound and examination support a confirmed uncomplicated cyst: small, symptom-free, and without a suspicious solid component, calcification, abnormal vascularity, suspicious lymph nodes, infection, or pressure on swallowing or breathing. It is one of the thyroglossal cyst treatment options, not proof that the cyst has been permanently treated.
Follow-up means measuring the lump and tracking symptoms, attending repeat clinical reviews, and having another ultrasound when advised. Report any of these promptly:
- Rapid growth
- Fever, redness, or new pain
- Persistent fluid drainage through the skin
- Difficulty swallowing
- Difficulty breathing
Observation is not risk-free. The cyst can enlarge, become infected, form an abscess, or create a draining sinus. Surgery after inflammation or repeated infection can involve more difficult dissection. Long-term evidence for observation is also less developed than evidence for surgical excision.
Do not choose watchful follow-up if you cannot reliably return for review or if the diagnosis remains uncertain. Malignancy is uncommon, but suspicion rises when the lump becomes hard, fixed, rapidly enlarges, or develops a solid component. Those findings require prompt reassessment rather than routine observation, often including further imaging or needle sampling.
When is the Sistrunk procedure safer than aspiration or simple excision?
The Sistrunk procedure is safer than aspiration or simple excision when a thyroglossal cyst is persistent, recurrent, infected repeatedly, enlarging, or causing symptoms. It removes the cyst, its thyroglossal duct tract, and the central portion of the hyoid bone, addressing tissue that limited surgery leaves behind.
| Option | What it removes | Main limitation |
|---|---|---|
| Sistrunk procedure | Cyst, duct tract, and central hyoid portion | Operative risks and recovery |
| Simple excision | Visible cyst only | Residual tract tissue can cause recurrence |
| Needle aspiration | Cyst fluid | The lining and tract remain, so fluid can return |
Commonly cited recurrence is about 5–10% after Sistrunk surgery versus roughly 45–55% after simple excision. Your risk depends on anatomy, previous infection, and earlier surgery, so these figures are not personal predictions. Aspiration remains useful for selected diagnostic sampling or short-term relief, but it is rarely definitive.
If infection is present, antibiotics come first; drain an abscess when necessary. Surgeons usually delay definitive Sistrunk surgery until acute inflammation settles, because operating through infection makes dissection harder.
Discuss bleeding or haematoma, wound infection, scar problems, anaesthetic complications, injury to nearby structures, and recurrence before surgery. These issues matter when comparing thyroglossal cyst treatment options or researching neck cyst surgery in Mumbai. A head-and-neck surgeon should also review recurrent disease rather than repeat limited excision automatically.
What tests determine whether surgery or observation is safe?
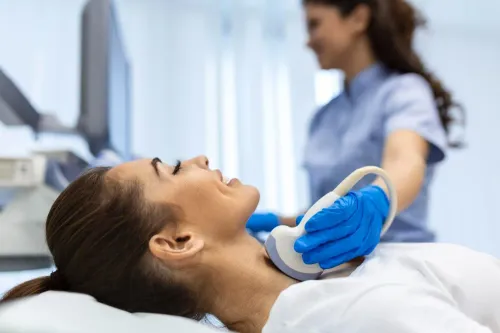
Ultrasound is usually the first test because it distinguishes a fluid-filled cyst from a lesion containing solid tissue. It assesses margins and calcification, examines cervical lymph nodes, and confirms that thyroid tissue sits normally in the neck.
That confirmation matters: rarely, a thyroglossal lesion contains the patient’s only functioning thyroid tissue, and removing it can cause hypothyroidism.
| Test | What it shows | When it matters |
|---|---|---|
| Ultrasound | Cystic or solid areas, margins, calcification, vascularity, lymph nodes, and normally located thyroid | Before deciding on observation or surgery |
| Thyroid-function tests | Thyroid hormone and TSH status | When the ultrasound or clinical assessment raises concern about thyroid function |
| CT or MRI | Depth, extent, tract anatomy, and nearby structures | An unusually deep, large, recurrent, infected, or anatomically unclear lesion |
| Fine-needle aspiration | Cells that can identify papillary thyroid carcinoma | An adult neck mass or a mural nodule, solid tissue, calcification, abnormal vascularity, or suspicious nodes |
Fine-needle aspiration is not needed for every classic, uncomplicated cyst. Papillary thyroid carcinoma is uncommon, often cited at about 1% of thyroglossal cysts, but a benign aspirate does not override examination and imaging. Suspicion can change an isolated Sistrunk procedure into additional thyroid or neck surgery.
For thyroglossal cyst surgery or observation in Mumbai, ask a thyroglossal cyst specialist in Mumbai which findings support waiting and which require tissue diagnosis or broader surgery. A scan, not the lump’s appearance alone, should guide that decision.
How should you choose a Mumbai specialist and plan follow-up?
Choose a surgeon who treats the decision, not just the lump. Mumbai does not change the safety standard: diagnosis, ultrasound, infection control, thyroid assessment, surgery, and follow-up matter more than location.
| Option | What it means | When it applies |
|---|---|---|
| Observation | Reviews, symptom monitoring, and repeat ultrasound when advised | Confident diagnosis, no symptoms, and dependable follow-up |
| Sistrunk procedure | Removes the cyst, central hyoid bone, and duct tract; usually under general anaesthesia | Symptoms, recurrence, infection, suspicious findings, or uncertainty |
| Aspiration or simple excision | Temporary fluid removal or limited cyst removal; residual lining or tract can remain | Selected sampling or short-term relief, not usually definitive treatment |
Take this checklist to your consultation:
- Ask whether the diagnosis is secure and whether ultrasound shows normally located thyroid tissue.
- Ask whether infection needs antibiotics or abscess drainage before surgery.
- Ask whether aspiration or fine-needle cytology is indicated, especially for an adult mass or solid, calcified, vascular, or nodal findings.
- Confirm the planned operation and ask whether the removed specimen will undergo histopathological examination.
- For recurrence, bring previous operative notes and imaging; residual tract tissue may require more than repeated limited removal.
- Ask about anaesthesia support, wound care, review dates, recurrence risk, and urgent symptoms such as fever, bleeding, breathing difficulty, or worsening swelling.
Dr. Navalakhe ENT Clinic can provide coordinated ENT and head-and-neck assessment for imaging, infection, surgery, and pathology. For neck cyst surgery in Mumbai, observation is safer for a confidently diagnosed, symptom-free cyst with reliable follow-up; definitive surgery is safer when symptoms, recurrence, infection, suspicious findings, or uncertainty make waiting more dangerous.
Related service
Head-Neck presents as a cystic midline neck swelling usually affecting young children but can occur at any age. View service → |
Frequently asked questions
Which option is safer for a child or adult: observation or surgery?
Observation has lower immediate risk for a small, symptom-free cyst with reassuring ultrasound findings and dependable follow-up. Surgery becomes safer when the cyst enlarges, recurs, causes symptoms, becomes infected or has suspicious features.
When is observation reasonable, and what risks remain?
Observation is reasonable when ultrasound shows a simple cyst without a solid component, airway problem or swallowing difficulty. The cyst can become infected, enlarge, recur or rarely contain malignancy, so follow-up remains essential.
When is the Sistrunk procedure safer than aspiration or simple excision?
The Sistrunk procedure is safer for a confirmed or strongly suspected thyroglossal duct cyst because it removes the cyst, central hyoid segment and duct tract. Aspiration often leaves the tract behind, while simple excision has a higher recurrence risk.
What tests determine whether surgery or observation is safe?
Assessment usually starts with a neck examination and ultrasound. Your specialist may add thyroid-function tests, imaging or fine-needle aspiration when the mass is solid, complex, enlarging, adult-onset or otherwise suspicious.
How should you choose a Mumbai specialist and plan follow-up?
Choose an ENT or head-and-neck surgeon who evaluates children and adults, explains ultrasound findings and offers a clear follow-up plan. Confirm who reviews pathology, when wound checks occur and which symptoms require urgent contact.
Keywords