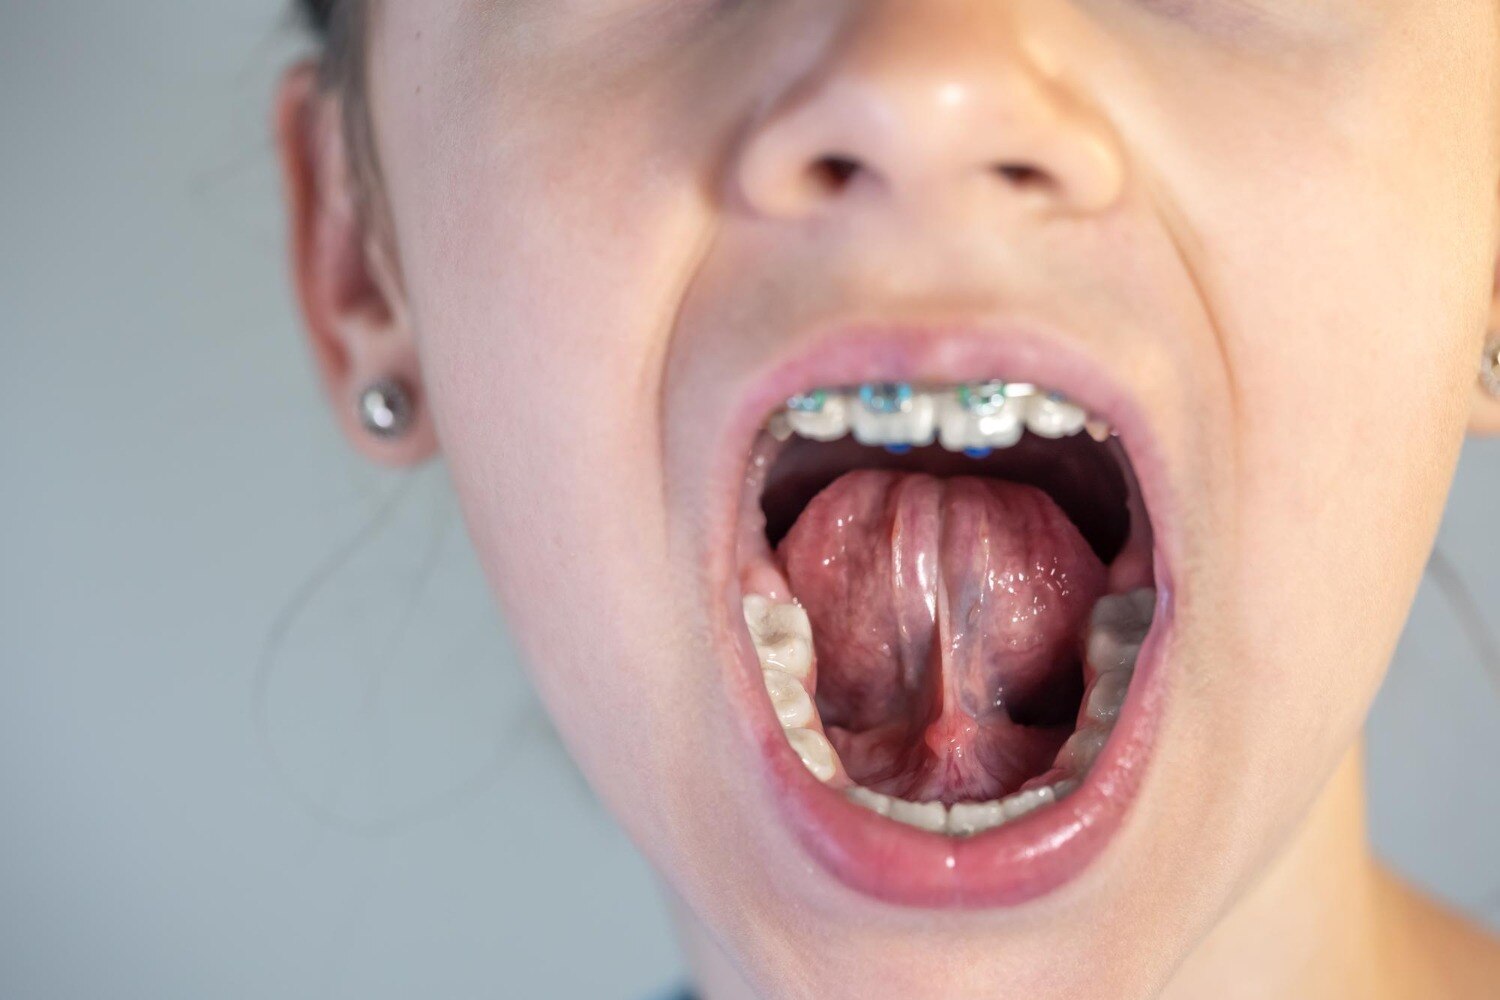
Feeding difficulty, clicking, nipple pain, or a heart-shaped tongue tip can raise concern about tongue tie, but none of these findings alone proves that a procedure is needed. By the end, you will know what a meaningful assessment involves, which alternatives must be checked, and how doctors decide between observation, feeding support, and treatment.
Key takeaways
- Feeding difficulty, dehydration, fatigue, and poor weight gain need prompt assessment.
- A visible frenulum alone does not prove that treatment is necessary.
- Ask about feeding support and observation before considering tongue tie surgery.
- Choose a pediatric ENT specialist who assesses function, not appearance alone.
How can you tell whether a newborn’s tongue tie is affecting feeding?
A newborn’s tongue tie warrants assessment when restricted tongue movement is disrupting feeding, not simply because a frenulum is visible. Seek prompt pediatric advice for breastfeeding pain, dehydration, poor weight gain, or persistent feeding fatigue.
Other warning signs include a shallow or slipping latch, clicking, milk leaking from the mouth, unusually long feeds, and a tongue that cannot lift or protrude; a heart-shaped tip can support the concern.
| Finding | More consistent with | What to do |
|---|---|---|
| Normal frenulum variation | A visible or slightly prominent band, with good tongue elevation, effective latch, comfortable feeds, and steady weight gain | Continue routine monitoring; appearance alone does not require treatment |
| Functionally significant restriction | Limited lift or protrusion alongside poor latch, clicking, leakage, prolonged feeds, maternal nipple pain, fatigue, or inadequate gain | Arrange feeding and oral-function assessment before considering treatment |
| Suspected posterior tongue tie | Subtle or unseen restriction near the tongue’s base, with feeding problems but no reliable appearance-based diagnosis | Ask the clinician to demonstrate restricted movement and assess alternatives; the term itself remains clinically controversial |
A tongue tie doctor in Mumbai should observe a feed, review the baby’s weight trend, and examine tongue elevation, protrusion, and coordination. Poor feeding can also result from prematurity, low muscle tone, nasal blockage, reflux, or milk-supply and positioning problems. A lactation assessment helps separate these causes.
Adequate feeding and growth usually support nonsurgical support and observation rather than immediate surgery.
What will a pediatric ENT doctor check before diagnosing tongue tie?
Before recommending surgery, a pediatric ENT doctor in Mumbai should establish that restricted tongue function—not simply a visible frenulum—is causing the feeding problem. The assessment combines history, examination, feeding observation and the baby’s weight trend.
1. Review feeding history: ask about latch, feed duration, clicking, milk leaking from the mouth, maternal nipple pain or trauma, fatigue, vomiting and the number of wet nappies. Observe breastfeeding or bottle-feeding when possible to assess milk transfer and positioning.
2. Check growth over time, not one isolated weight. Falling across growth centiles, dehydration or inadequate intake makes prompt feeding support important, but these findings do not prove tongue tie.
3. Examine tongue elevation, protrusion, side-to-side movement and the shape of the tongue tip, then inspect the frenulum and mouth. A scoring tool such as the Hazelbaker Assessment Tool or Bristol Tongue Assessment Tool can support the examination; neither replaces it.
4. Look for other explanations, including poor positioning, low milk supply, prematurity, reflux, nasal obstruction, high palate, oral-motor difficulty or illness. A lactation professional can assess feeding, while a speech-language professional can assess oral-motor or speech concerns when relevant.
A posterior tongue tie diagnosis deserves particular care because clinicians disagree about its definition and appearance alone cannot establish it. Surgery should follow demonstrated, persistent functional impairment after nonsurgical support—not a photograph or an anatomical label.
When is observation or nonsurgical support better than a procedure?
Adequate milk transfer, comfortable feeding, and steady weight gain support observation rather than an immediate procedure. A visible frenulum does not require treatment when the baby feeds effectively; positioning, latch adjustment, paced feeding, and review of other causes can solve the problem without cutting tissue.
For parents searching “tongue tie treatment baby in mumbai,” ask what measurable problem the procedure is expected to correct. Frenotomy has the clearest evidence for reducing some mothers’ nipple pain, but consistent improvement in milk transfer or long-term breastfeeding is not established.
Do not choose release solely to prevent future speech, sleep-apnoea, dental, or feeding problems in an otherwise asymptomatic child.
Treatment deserves discussion when restricted tongue movement continues to cause a documented functional problem despite skilled support. The plan should bring the right professionals together:
- A lactation professional observes a feed, checks latch and milk transfer, and helps correct positioning before surgery is considered.
- A pediatrician tracks hydration, illness, feeding fatigue, and weight over time; poor gain requires prompt medical review.
- A speech-language professional assesses speech or oral-motor function in an older child, while a pediatric ENT clinician evaluates movement and anatomy.
Persistent inability to elevate the tongue, difficulty clearing food, mechanical interference with brushing, or a speech problem confirmed by assessment gives treatment a stronger rationale than appearance alone.
What do frenotomy, frenectomy, and frenuloplasty involve?
Frenotomy makes a small cut to divide the restrictive lingual frenulum; frenectomy removes more of the frenulum, while frenuloplasty releases it more extensively and closes or rearranges the wound. Surgeons do not use these terms identically, so ask what tissue will be released and why.
| Procedure | Typical approach | Stitches and instruments |
|---|---|---|
| Frenotomy | Quick division, often for a newborn with persistent functional feeding difficulty | Usually scissors or a sterile blade; stitches are uncommon |
| Frenectomy | Wider removal of frenulum tissue | May require stitches; the instrument depends on anatomy and clinician preference |
| Frenuloplasty | Larger release with wound closure or tissue rearrangement | Stitches are usually needed; local or general anaesthesia depends on age and cooperation |
For a newborn, the clinician may use topical or local anaesthesia, or no anaesthetic for a very brief release, followed by feeding. An older child usually needs local anaesthesia if cooperative; general anaesthesia is considered when cooperation, anatomy, or the planned repair requires it.
Before consenting to tongue tie surgery in Mumbai, ask these questions:
- What measurable problem will this release address, and how will improvement be assessed?
- Is conservative feeding or speech support still appropriate?
- What pain relief, feeding plan, and follow-up are included?
- Do the wound and stitches need specific care?
Expect brief pain, a small amount of bleeding, and a healing wound. Infection, persistent restriction, scarring, reattachment, feeding aversion, or injury to nearby tissue are uncommon but possible. Feed according to the clinician’s instructions, attend review, and perform wound movements only when specifically advised; surgery cannot guarantee better breastfeeding, speech, sleep, or future dental outcomes.
How should you choose a tongue tie specialist in Mumbai?
Choose a tongue tie specialist in Mumbai who evaluates function rather than offering surgery from a photograph. Ask the clinician to demonstrate restricted tongue elevation or protrusion, explain how the finding relates to feeding or speech, and discuss other causes before recommending a procedure.
| Question to ask | What a useful answer includes | Warning sign |
|---|---|---|
| What problem will treatment correct? | A measurable goal, such as less nipple pain, better milk transfer, easier food clearing or improved tongue movement | “It will improve everything” |
| What are the alternatives? | Lactation support, feeding review, observation, pediatric care or speech-language assessment | Surgery is presented as the only option |
| How will improvement be measured? | Weight trend, feeding observation, pain score, tongue movement or a documented speech or oral-motor concern | A healed wound is treated as proof of success |
| What follow-up is included? | Review of feeding, pain, movement and reattachment, with clear instructions for contacting the clinic | No planned review or aftercare explanation |
| What are the risks? | Bleeding, infection, pain, feeding refusal, injury to nearby structures and recurrence or reattachment | Risks are dismissed as impossible |
Because “posterior tongue-tie” lacks a consistent definition, ask how the clinician diagnosed functional restriction and what non-surgical explanations were excluded.
A practical referral may include pediatric ENT assessment, a lactation professional for feeding, and a speech-language professional for relevant speech or oral-motor concerns. Dr. Navalakhe ENT Clinic can be considered when its assessment explains these roles, expected outcomes and follow-up rather than relying on procedure marketing.
Related service
Pediatric Ent (ankyloglossia) is characterised by tethering of the anterior part of the tongue to the floor of mouth by short lingual frenulum. View service → |
Frequently asked questions
How can you tell whether a newborn’s tongue tie is affecting feeding?
Look for breastfeeding pain, shallow latch, clicking sounds, prolonged or tiring feeds, poor milk transfer, dehydration, and poor weight gain. A visible frenulum does not establish that tongue tie is causing the problem.
What will a pediatric ENT doctor check before diagnosing tongue tie?
The doctor will assess tongue movement, lift, extension, attachment of the frenulum, oral anatomy, latch, milk transfer, weight trend, hydration, and other causes of feeding difficulty. A feeding assessment can help connect restricted movement with symptoms.
When is observation or nonsurgical support better than a procedure?
Observation or feeding support is appropriate when the baby is gaining weight, staying hydrated, feeding effectively, or when symptoms have another likely cause. Lactation support and follow-up can clarify whether restriction is functionally important.
What do frenotomy, frenectomy, and frenuloplasty involve?
A frenotomy releases the tight tissue with a small incision. A frenectomy removes more of the frenulum. A frenuloplasty releases and repairs the area with a planned wound closure, usually when more extensive restriction requires it. The doctor should explain pain control, bleeding, feeding, wound care, and follow-up.
How should you choose a tongue tie specialist in Mumbai?
Choose a pediatric ENT doctor who examines feeding and tongue function, discusses nonsurgical options, explains the exact procedure and risks, and provides follow-up. Ask how lactation support, weight checks, pain control, and post-procedure concerns are handled.
Keywords